Dr Louisa Sun · Division of Infectious Diseases, Alexandra Hospital, Singapore
The Preparedness Lab
Flatten the Curve... for Learning
Interactive tools for teaching public health, outbreak preparedness and response. Each one puts the learner in front of a decision, and then shows them what it cost.
Working under uncertainty, weighing containment against livelihoods and trust, judging when the evidence is strong enough to act: these are the hardest parts of outbreak response, and they are rarely learned well from being told about them. They are learned by deciding under pressure and then living with the result, even when the result is simulated.
If you teach or design training in this field, the tools here are free to use in non-commercial teaching, apart from two that are used by written permission, and most of them can be adapted to a different context, audience or pathogen.
14interactive tools for teaching
6teaching programmes they were built for
3formats — multiplayer, self-paced, exercise series
Teaching tools
Built to make learners decide
The tools here are proof of concept as much as finished products. Each one started from a specific teaching problem, such as a concept that learners did not grasp from a lecture or a skill that can only be acquired through practice.
They have been used in postgraduate classrooms and professional training settings, and adapted for different regional contexts and audience levels. Many other teaching problems would suit the same approach.
Coverage of the course of an outbreak, by toolShow figureHide figureThe axis runs from the first signal to recovery, and each bar marks the part of an outbreak that the tool covers. The exercise series covers the whole course because its cases are drawn from the history of public health, and several of them are not outbreaks.
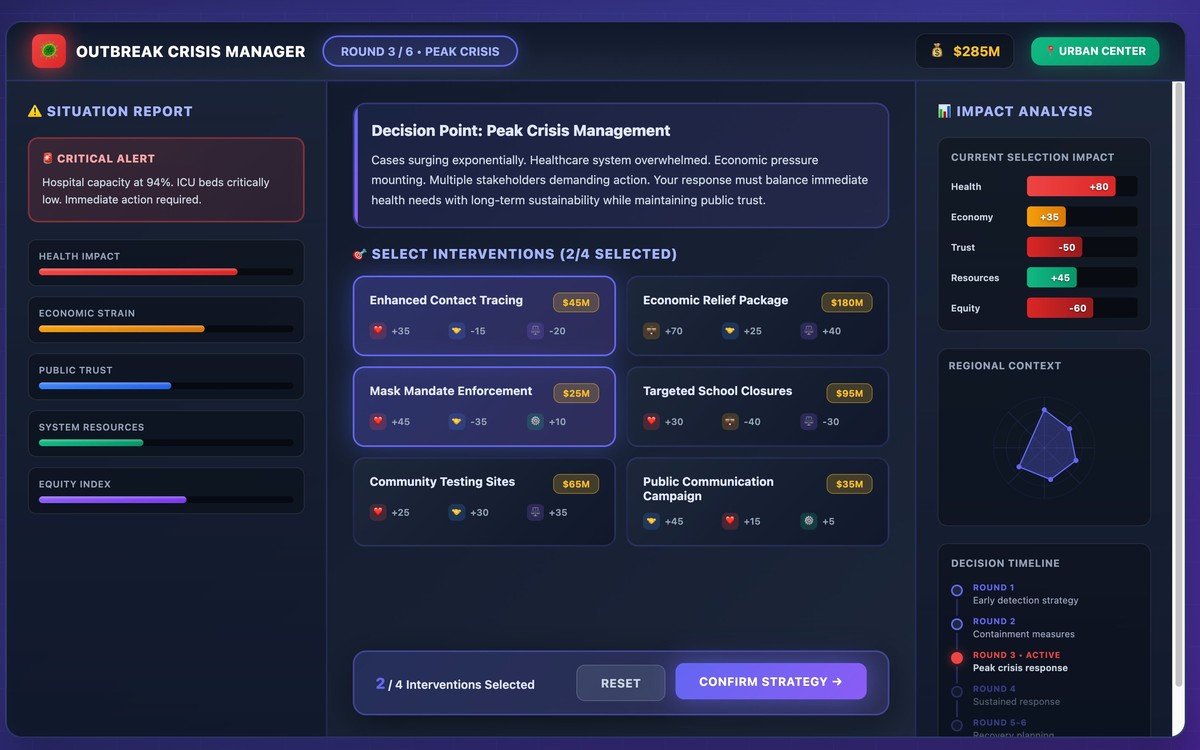
The simulation runs for six rounds, which follow the outbreak from the first unexplained cases to the end of the emergency. In each round the player selects non-pharmaceutical interventions within a budget, and each intervention has effects on five measures: health, economy, public trust, resources and equity. The five regions differ in population, economy, vulnerabilities and political constraints, and the same intervention therefore has a different effect in each region. Three stakeholder groups make requests with deadlines, and misinformation events occur in some rounds.
The interventions that reduce transmission most also carry the largest economic and social costs, and a response that is sound on the evidence can lose the region's political support.
Design logic
Effects are shown as directional arrows instead of points, so that the player reasons about trade-offs rather than optimising a visible score. Evidence strength, regional fit, preparedness, stakeholder escalation and misinformation all modify what an intervention costs or achieves. The single-player edition ends early under two conditions: epidemic overload, when hospital capacity is exceeded, and loss of political mandate, when the regional assembly withdraws the emergency powers.
Format
The single-player edition runs in the browser, without installation or accounts. In the facilitated multiplayer version, five regional teams play in one room with timed rounds and a facilitator's view.
Features and licence
Stakeholder pressure systemThree stakeholder groups escalate their demands across rounds, and a group that is neglected can block specific interventions.
Preparedness consequence engineDecisions in early rounds carry forward and produce region-specific benefits or penalties later in the game.
Evidence-tier frameworkEach intervention is tagged with the strength of its evidence, which modifies what it costs or achieves.
Misinformation challenge mechanicMisinformation events arise partway through a round and disrupt the teams' strategy.
Community-led alternativesEvery round includes zero-cost grassroots options alongside government interventions.
After-action debriefThe debrief reports the downstream consequences of each team's decisions across all six rounds.
Regional and pathogen parameters can be adapted to other outbreak scenarios. The engine has been re-themed once, into The Forest Edge.
Simulation · single-player and facilitated multiplayer
The Forest Edge
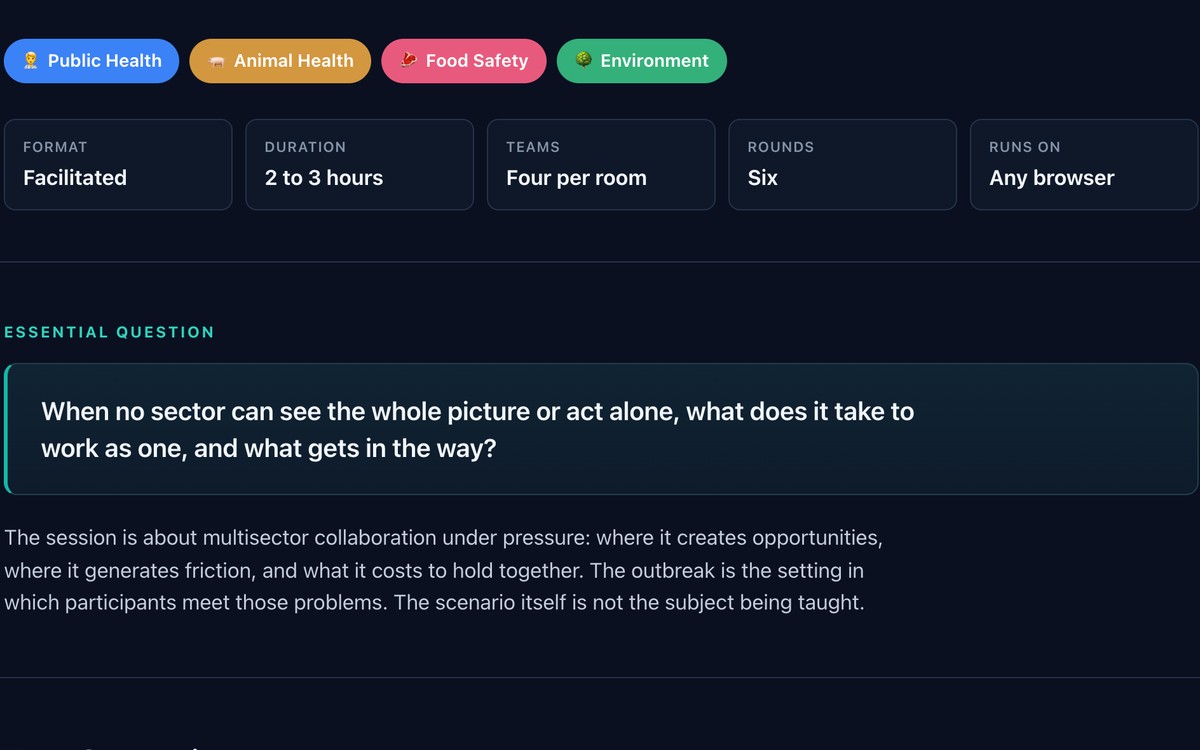
The Forest Edge is a One Health field investigation simulation in which four sectors (Public Health, Animal Health, Food Safety and Environment) respond to a zoonotic outbreak over six rounds.
Each sector holds only part of the information, field teams, budget and authority needed to control the outbreak, and confirming the source requires evidence that no single sector can obtain alone: the virus in human samples, the virus in the animal source, and an analytic study. In each round a sector reviews the situation and its own signals, resolves a crisis, allocates field teams and budget to investigations and control measures, and commits its decisions. The round then closes, and the report shows what changed and what the other three sectors did.
In the single-player edition the player holds one sector and the other three are run by the computer. Their leads report what they see and what they intend, and their findings appear on a shared board once they have investigated. Each round one of them makes a request with a deadline, and a request that is met leads to coordination in the following round. Each round's crisis is put to the player by the person who raises it, with three possible answers where the facilitated version offers two, and an answer can also have a consequence a round later. In the facilitated version, run as the scenario Spillover at the Forest Edge, four teams hold the sectors and the facilitator resolves each round on a board visible to the whole room.
Design logic
The effect of a control measure is proportional to what the four sectors have confirmed about the source and to public trust, so a measure taken before the source is understood achieves only a fraction of its effect, and additional spending does not compensate. The outbreak, public trust and the economy are shared by all four sectors, and no sector has a score of its own, so a shortcut taken by one sector imposes costs on the other three.
Format
Single-player edition in the browser. The facilitated version runs for 2 to 3 hours with four teams and a facilitator; its materials comprise a run guide with per-round guidance and a debrief script, participant briefs and role cards, teaching decks, and a sourced evidence pack. The pathogen is not named to participants until the debrief.
Features and licence
Each team sees only its own sectorA team is shown only its own sector's signals and resources. Information established by the other sectors reaches it only through communication.
Measures depend on what has been confirmedA control measure taken before the source is understood achieves only a fraction of its effect, and additional spending does not compensate for an incomplete investigation.
Severity, trust and livelihoods are tracked separatelyContainment achieved through coercion registers as lost trust and lost income, and low trust then reduces compliance with every subsequent measure.
Budget and field teams are finiteThere is one budget for the whole outbreak, a small number of field teams each round, and a share of a single national laboratory; budget spent early is unavailable at the peak.
Forced decisionsEach round presents each sector with one forced decision, and declining to decide costs more than any of the options.
Frameworks are named in the debriefParticipants play first; the frameworks are introduced in the debrief against decisions the participants have already made.
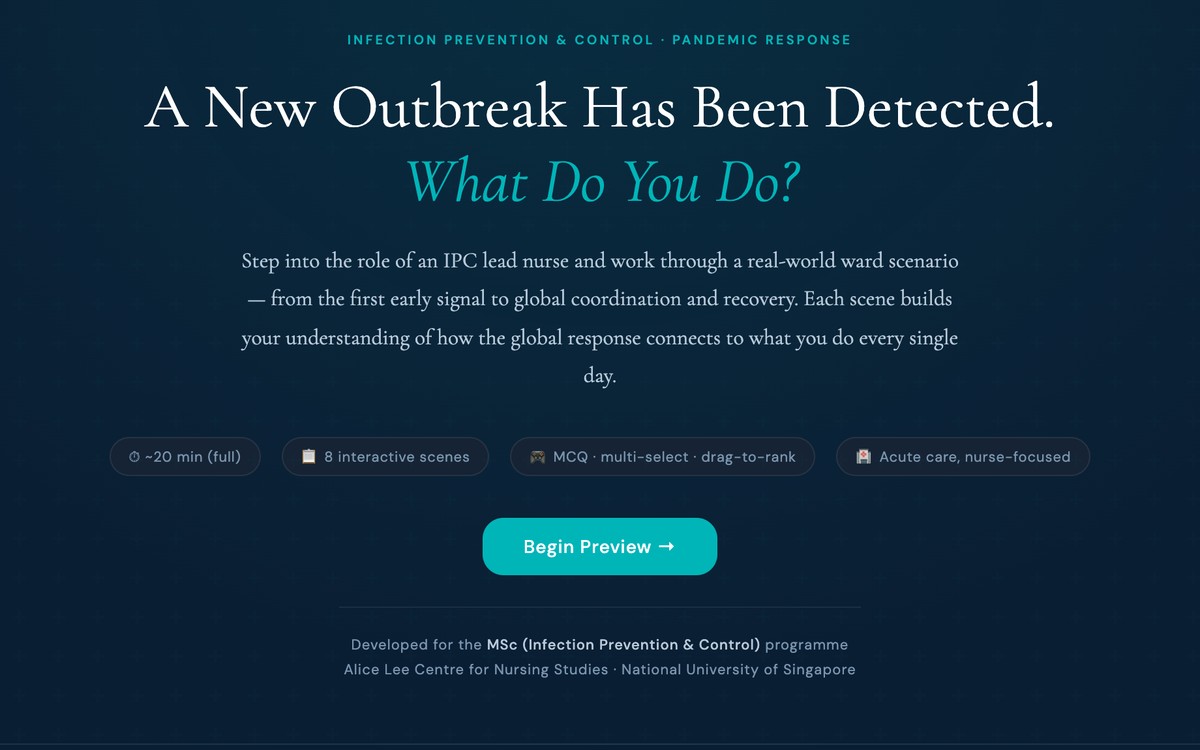
The player takes the role of the IPC lead nurse on a hospital ward and follows an outbreak through eight scenes, from the first ward signal, through preparedness, the response pillars, genomics and global coordination, to recovery. Each decision connects events on the ward to the national and global systems that act on them and return guidance to the bedside. The simulation was developed for the MSc in Infection Prevention and Control at the Alice Lee Centre for Nursing Studies, National University of Singapore.
Design logic
Each scene ends in a decision, taken as a multiple-choice or multi-select question or a drag-to-rank sequence, and the feedback after each decision states the key learning point. Expandable knowledge cards explain, at the point of use, the concepts on which a scene rests, such as the Swiss cheese model and the International Health Regulations. The language and the scenarios are those of ward-based staff.
Format
Self-paced, about 20 minutes, in the browser.
Features and licence
8 scenesThe scenes run from the first signal to recovery and cover preparedness, the response pillars, genomics and global coordination.
Multiple-choice and multi-select questionsEach decision is followed by detailed feedback and a key learning point.
Drag-and-drop sequencingA sequencing task traces how a ward report becomes global guidance and returns to the bedside.
Knowledge cardsExpandable panels explain core concepts, such as flattening the curve and the Swiss cheese model.
Built for nursing educationThe simulation aligns with IPC learning outcomes and uses language and scenarios familiar to ward-based staff.
Self-contained and self-pacedThe simulation runs entirely in the browser and can be used for individual study or with a facilitated group debrief.
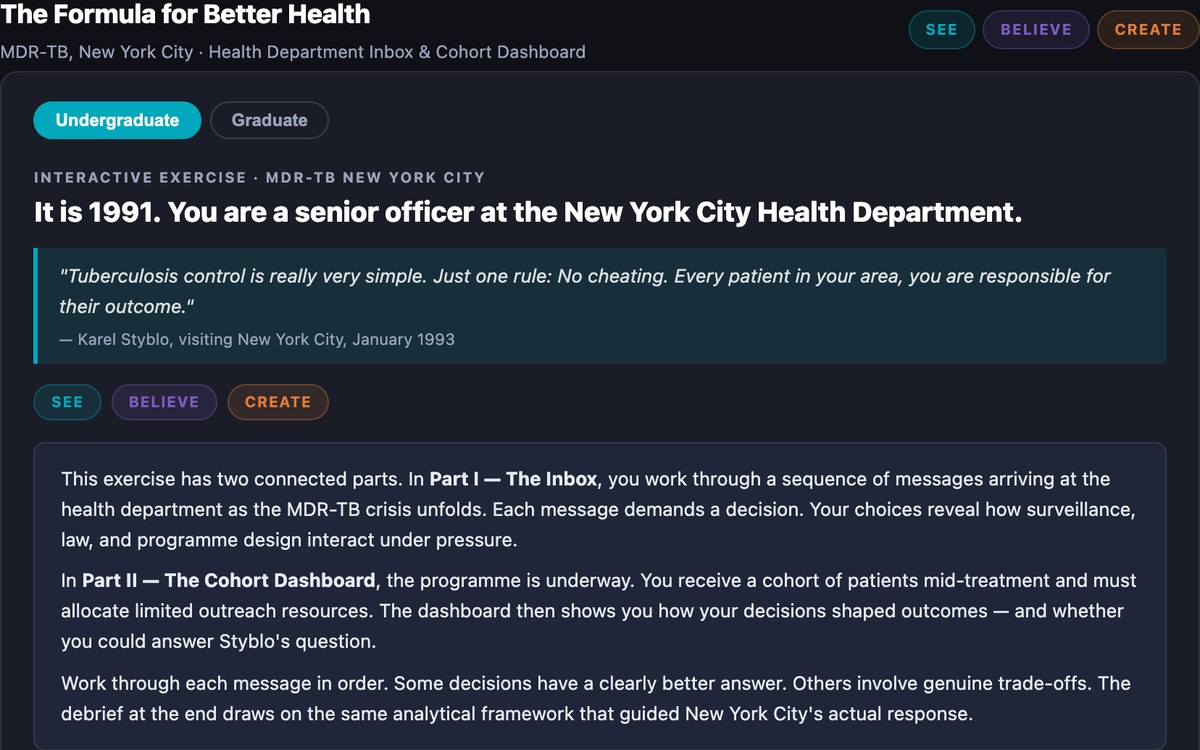
Each exercise places the learner in the position of a decision-maker in a documented case from the history of public health and requires a decision to be committed before the reasoning is revealed. The case studies and the teaching content are Dr Frieden's; the contribution here is the exercise design, which turns each case into a sequence of decisions. Each exercise runs in an undergraduate and a graduate mode on the same material and takes about 15 minutes; it can be used on its own or within a course.
Design logic
Learners commit a choice and record their assumptions before the reasoning is revealed, so that the debrief can be checked against their own choices and assumptions. Decisions carry forward across the acts of a case, and a consistency check identifies contradictions between a learner's analysis and the design decisions that follow it. The inbox and cohort-dashboard formats reproduce the information environment of the decision-maker in the original case.
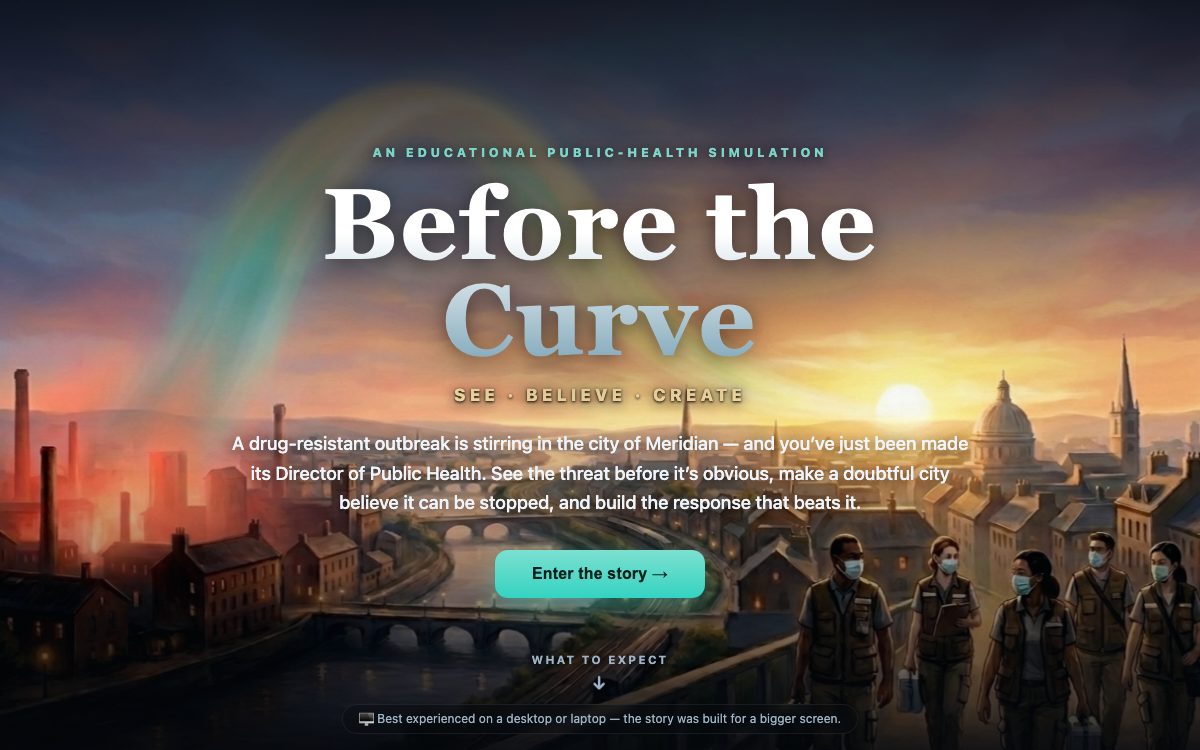
Before the Curve is a single-player narrative simulation of the public health response to a drug-resistant respiratory outbreak in a fictional city, with the player as its Director of Public Health. The three acts follow the See, Believe and Create framework of The Formula for Better Health.
The city, Meridian, has 600,000 inhabitants, and the player is appointed as the first cases appear in a single working-class district. In the first act, See, the player decides which weak signals to investigate and when the evidence is sufficient to act; in the second, Believe, how to build public and political confidence that the outbreak can be stopped; in the third, Create, how to design a response that is fast and fair, with each part of it assigned to a named person. Each decision is made by playing one card from a hand of options, after which the epidemic curve and the player's standing with the main characters are updated on screen. Decisions cannot be reversed, and their consequences carry through to the end.
Design logic
Every decision is committed before the reasoning behind it is revealed. Each decision corresponds to a principle from the book, and that principle's page is added to the player's collection when the decision is made. The debrief traces the outcome back through the player's own choices.
Format
Self-paced, about 60 minutes in total, in three acts of roughly equal length, played in the browser on a desktop or laptop; progress is saved and can be resumed. The simulation is suitable for courses from introductory to graduate level and can be used as a standalone activity or alongside the existing case studies. No prior public health study is assumed, and technical terms are defined where they first appear.
Decisions are irreversibleNothing can be undone, and the consequences of early decisions persist to the end of the three acts.
Terms are defined at first useTechnical terms carry a definition on hover or tap.
Counterfactual curveThe player's epidemic curve is plotted against a do-nothing baseline, and the gap between the two is shown as cases prevented. During play the curve also carries a forecast that changes with each decision.
Progress is savedThe simulation saves at each scene and resumes at the same point.
Investigation game · single-player
Trainee at Outbreaks Central
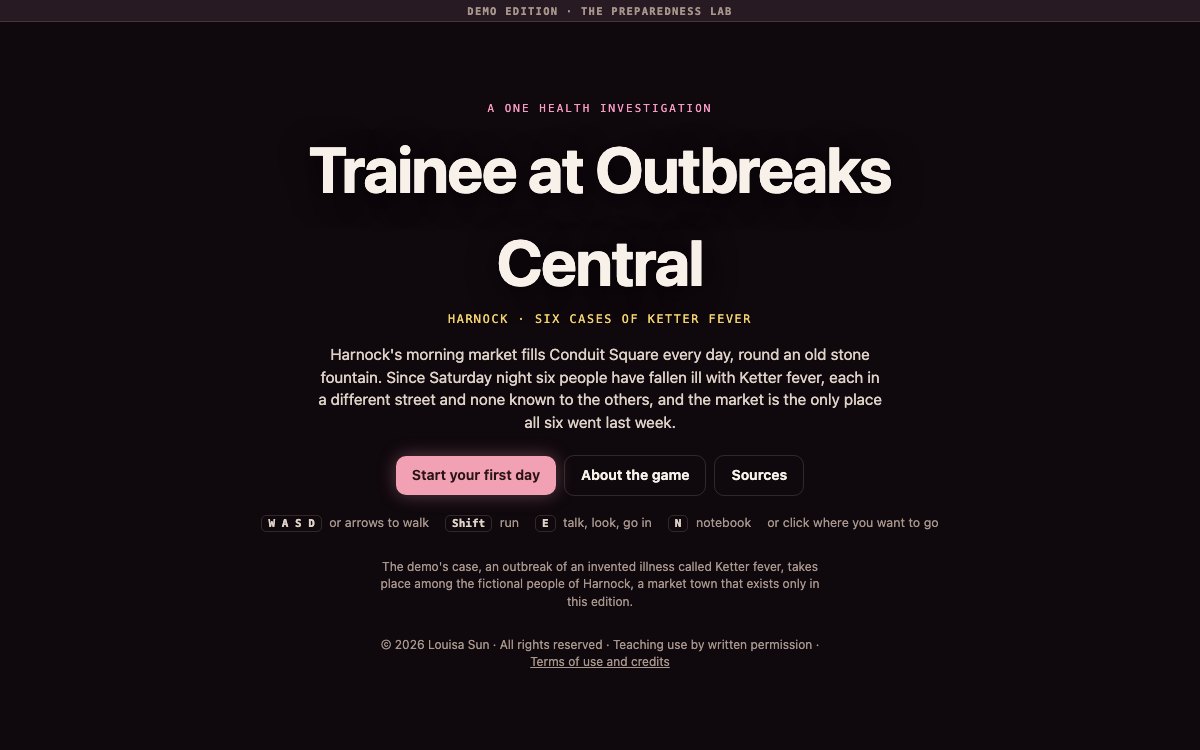
Trainee at Outbreaks Central is an investigation game in which the player, a trainee at a public health office, traces a foodborne outbreak using evidence held by four One Health offices.
Over one in-game week, three people are infected through food, each by a different route, and the player investigates each infection as a separate case. The player walks through the town, inspects kitchens, interviews residents, submits samples to a laboratory that processes four a day with a turnaround of about four hours, and assembles evidence held separately by four offices. An investigation closes when its case file is answered correctly, and the week ends with a debrief that reviews the three cases and lists every finding, including those the player missed.
Design logic
The trainee has responsibility for the case but no authority over the four offices, so remedial action follows only when the responsible office is presented with evidence on which it can act. One Health is taught through the coordination problem itself, and the four modes of inter-agency working (collaboration, coordination, communication and capacity building) are scored at the end of the week.
Format
Single-player, in the browser on a desktop or laptop with the keyboard and mouse, or on a phone or tablet by touch. Progress is saved and can be resumed, and the debrief can be printed.
Features and licence
Time-based mechanicsResidents keep their own hours, and a laboratory result takes about four hours.
TrustResidents disclose more as their trust in the trainee increases, and trust varies with how they are treated.
Evidence held by four officesEach office holds one part of the answer, and the trainee assembles the parts.
Evidence rulesA negative laboratory result excludes a dish; a positive result closes a link in the chain of transmission.
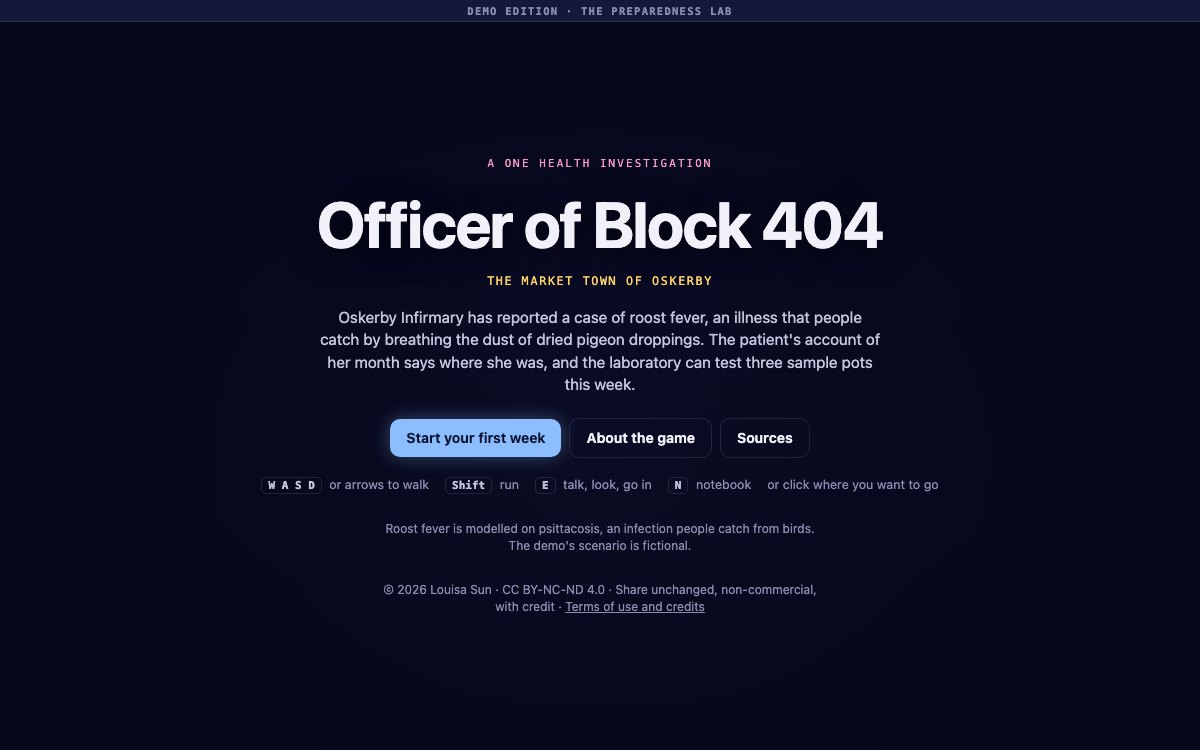
Officer of Block 404 is an investigation game in which the player, the newly appointed officer of a public housing estate, establishes how a cluster of leptospirosis arose among the people who live and work there.
Over one in-game month, three people on the estate fall ill, and for each of them the player reconstructs the exposure that caused the infection, including where and when it occurred. The player walks the estate, inspects its shared spaces, interviews residents and workers and sends samples to a laboratory. Most of the repairs that would prevent further cases are the responsibility of four other offices, and each office has to be shown the evidence for its part. Time runs while the player moves about the estate, and it stops whenever a screen of text is open.
Design logic
The player has responsibility for the estate but limited authority over the offices that must act, and One Health is taught through that coordination problem. Environmental persistence of the organism, the routes of exposure, the incubation period, occupational risk and targeted testing each bear on how a case is solved.
Format
Single-player, in the browser on a desktop or laptop with the keyboard and mouse, or on a phone or tablet by touch. Progress is saved and can be resumed, and the debrief can be printed. The game is designed for members of the public and for learners without specialist training.
Features and licence
Time-based mechanicsResidents and offices keep their own hours, and a laboratory result returns an hour after the sample is sent.
TrustResidents disclose more as their trust in the officer increases, and they act only on advice from an office they have confidence in.
Repairs change the estateEach repair changes the ground the player walks on, so the effect of the response can be seen on the map.
DebriefThe month ends with a debrief that reviews the three cases and lists every fact in the notebook, marking those the player did not find.
Negotiation simulation · single-player and facilitated multiplayer
Movid-26
Movid-26 is a negotiation simulation for teaching global health diplomacy, in which five parties negotiate the allocation of a scarce medicine during a fictional outbreak.
5 rounds
5 per table
Up to 12 tables
90 to 120 minutes
Browser
Teaching use by written permission
Movid-26 has a single-player mode and a facilitated multiplayer version; the author can be contacted for details or access.
Three states, an international organisation and a manufacturer meet five times over the course of the outbreak, and an epidemic model runs on what they agree. The parties' combined requirements exceed the available supply, so a table that only divides what is available ends with every party below its requirement and the outbreak still in progress.
Each round is anchored to a provision of the International Health Regulations, and the dilemma of the round is the one that provision creates. Participants weigh their parties' interests against legal obligations under time pressure, and no party holds the full information.
Design logic
The simulation has no chat function, so negotiation takes place in the room. It also has no undo, and a notification, a public move or an agreed deal stands once it is made. The round ends when the facilitator closes it. The intended debrief compares the tables in a class, each of which has played the same outbreak with different decisions.
Formats
A whole class of up to twelve tables paced from one dashboard, a single table with a facilitator console, or one player against computer counterparties at three difficulty settings. All three run the same engine.
Access
Access is arranged by written permission of the copyright holders. Facilitator materials comprise a walkthrough, a player's guide and a features and mechanics document.
Features and licence
Confidential briefsEach party receives a confidential brief stating its holdings and the weaknesses and limits of its position. No party can reach its objectives alone.
Home-front decisionsCommitments made at the table must be carried out at home, through the party's own institutions, and a home-front decision left unanswered is settled without the party, on worse terms.
Time-limited optionsEach cooperative option closes at a fixed round, so a party that waits until the move appears affordable finds it no longer available.
Public movesA party may make one public move a round, and each one carries a cost.
The same approach applies wherever a learner needs judgement rather than recall, and the following problems in public health training would suit it.
Laboratory capacity and accreditation
Presenting accreditation standards to health workers as an interactive sequence of decisions, in place of a checklist or manual.
Public health workforce induction
Orienting new staff to outbreak protocols and institutional systems through scenario-based exercises that develop judgement as well as familiarity.
Risk communication practice
Designing messages for audiences with varying levels of trust, at different stages of an outbreak, with feedback that shows the consequences of each choice.
Further One Health exercises
Cross-sectoral teams managing other zoonotic spillover events, with mechanics that represent the human-animal-environment interface in operational terms.
Surveillance system design
Building a sentinel network under resource and time constraints, with competing priorities that require trade-offs.
Policymaker decision support
Translating outbreak modelling outputs and epidemiological evidence into decision-relevant formats for non-technical audiences.
Community and school-level education
Teaching epidemic dynamics to younger or non-specialist audiences through simulations that are simplified but keep the structure of the underlying model.
Dr Louisa Sun (MB BS, MMed (Int Med), MRCP(UK), MPH) is an infectious diseases and public health physician based in Singapore. She is Head and Consultant of the Division of Infectious Diseases at Alexandra Hospital, National University Health System, and a Visiting Consultant at the National Centre for Infectious Diseases.
Her clinical work spans infectious disease medicine, infection prevention and control, and antimicrobial stewardship. She has led outbreak response operations at the institutional level, including large-scale field response during the COVID-19 pandemic, and contributes to national public health policy across communicable disease governance and antimicrobial resistance. Globally, she is engaged in outbreak preparedness and response through the Global Outbreak Alert and Response Network (GOARN).
In education, she has contributed to the development and delivery of postgraduate programmes in infectious disease emergencies and infection prevention and control, and holds teaching appointments at the Yong Loo Lin School of Medicine, National University of Singapore.
Alongside this work, she develops interactive teaching tools for outbreak preparedness education.